
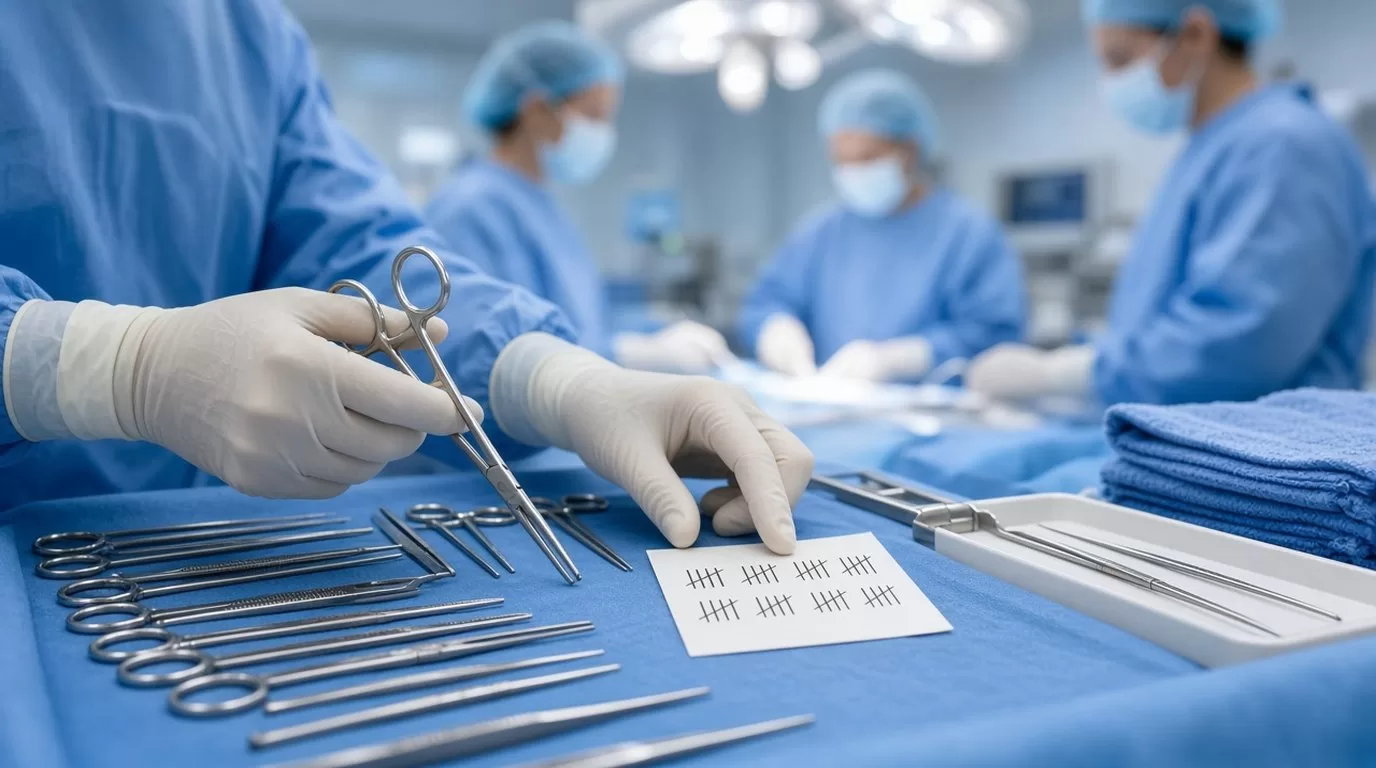
You know that moment when the surgeon is closing and the circulator asks, “Ready for final count?” Your heart rate ticks up just a little. You've counted three times already. Everything should be perfect. And yet — that tiny knot of anxiety sits right there in your chest until you hear “correct.”
If you're a surgical tech, you've lived this moment hundreds of times. The count is sacred, it's protocol, and honestly? It's a little bit personal. Because when it's off, the entire room goes into hyperfocus mode, and you're the one mentally retracing every step of the case.
Here are eleven things that only surgical techs truly, deeply understand about the count — the rituals, the anxieties, and the inside jokes that bond every scrub tech who's ever stood at a Mayo stand.
The Panic When Someone Says 'Wait, How Many Lap Sponges?'
It doesn't matter that you've been counting lap sponges for five years. The second someone questions the number, your brain does a full reset. You were confident thirty seconds ago. Now? You're counting again from scratch, touching each sponge like it's evidence in a court case.
According to The Joint Commission's National Patient Safety Goals, retained surgical items remain a “never event,” meaning they should never happen — and accurate counts are the first line of defense. That's why even the smallest discrepancy feels like the floor just dropped out from under you.
The truth is, most of the time it's a miscount on paper or a sponge that got kicked under the table. But until you find it, your entire nervous system is on high alert.
The Irrational Attachment to Your Count Board
Your count board isn't just a piece of laminated paper. It's your security blanket, your legal documentation, and your proof that you did everything right. Some techs have specific count board preferences — the grid style, the tally method, the color of the dry-erase marker.
You guard that board like it's classified information. If someone tries to erase a section before you've verified it with the circulator, you'll swat their hand away faster than you can say “radio-opaque.”
And heaven help the person who accidentally throws it in the trash. That board is your alibi if anything goes sideways post-op.
The Silent Dread of a Shift-Change Count
Shift changes during a case are nobody's favorite thing, but they're especially stressful when you're mid-procedure and have to hand off your count to the incoming tech. You've been tracking every needle, every blade, every tiny micro instrument — and now you have to trust someone else to pick up exactly where you left off.
The Association of Surgical Technologists (AST) emphasizes the importance of clear communication and documentation during hand-offs, because this is when count discrepancies are most likely to happen. You do the count together, you verify together, you document together — and you still worry a little bit after the other tech takes over.
It's not that you don't trust them. It's just that you know how easy it is for one small detail to slip through the cracks when attention shifts.
The Superstition Around Opening Extra Packs
Every surgical tech has a slight twinge of superstition when the surgeon asks for an extra pack of something mid-case. You know it's necessary. You know it's part of the job. But in the back of your mind, a little voice whispers: “More things to count. More things that could go missing.”
You open the pack, you add it to the board, and you make a mental note to triple-check that item during final count. Because if there's going to be a discrepancy, it's probably going to involve the thing that got added at the last minute when everyone's focus was on the surgical field.
The Moment You Realize a Sponge Is Inside the Patient
Not missing. Inside. On purpose. Because the surgeon is using it for retraction or packing, and they haven't removed it yet.
Your count is off by one. You know exactly where it is. But until it comes out and you can physically touch it and add it back to the pile, your documentation shows a discrepancy. You tell the circulator. You tell the surgeon. Everyone agrees. And you still feel that low-level hum of anxiety until the sponge is back on your Mayo stand and the count is correct again.
This is why radio-opaque markers and X-ray-detectable sponges exist — and why you love them with your whole heart.
The Ritual of Counting Needles Like Precious Gems
Needles are small. Needles are sharp. Needles have a tendency to hide in the folds of drapes, inside suture packages, or — worst case — on the floor. You count them at the beginning of the case, you count them after every single suture pass, and you count them again at the end with the intensity of someone defusing a bomb.
Some techs use needle mats. Some use magnetic boards. Some have a specific corner of the Mayo stand that is needle territory and needle territory only. Whatever your system, it's non-negotiable.
And if a needle goes missing? The entire room stops. Lights go up. Everyone checks their gloves, their gowns, the drapes, the floor. Because a retained needle isn't just a count problem — it's a patient safety emergency.
Common Needle Count Strategies:
- Magnetic needle mats that hold each needle in a visible slot
- Verbal confirmation with the surgeon after every suture pass
- Separate documentation for control-release needles vs. swaged-on
- Floor sweeps with a magnetic wand after every case
The Unspoken Bond When Count Is Correct on the First Try
When you and the circulator finish final count and everything matches — no discrepancies, no recounts, no drama — there's a tiny moment of mutual respect. You might exchange a glance. You might say “nice.” You might just nod.
But that feeling? That's the feeling of a job done right. It's the surgical tech equivalent of a high-five, and it never gets old.
The Guilt That Hits When You Have to Call for an X-Ray
Sometimes, despite your best efforts, you can't reconcile the count. You've checked everything twice. The surgeon has checked. The circulator has checked. The count is still off, and the patient is about to be closed.
So you call for an X-ray. It's the right call. It's the safe call. It's literally what the protocol says to do. And yet — you feel a pang of guilt, like you've somehow failed, even though you've done everything by the book.
The Bureau of Labor Statistics notes that surgical technologists are responsible for maintaining accurate counts as a core part of their role, and that responsibility comes with emotional weight. You take it seriously because you know what's at stake.
Most of the time, the X-ray shows nothing. The missing item turns up in the trash or on the back table. But you'd rather do ten unnecessary X-rays than risk a retained object.
The Satisfaction of Finding the 'Missing' Item in Plain Sight
And then there's the flip side: when you've been searching for a missing sponge for five minutes, and someone finally spots it — sitting right there on the corner of the back table, exactly where it should be, just hidden under a drape.
Relief floods in. Everyone laughs. The count is corrected. The case moves forward. And you make a mental note to arrange your back table differently next time.
The Inside Joke About 'Counting Anxiety Dreams'
Ask any surgical tech if they've ever had a dream about a count discrepancy, and at least half will say yes. You're in the OR, the count is wrong, and no matter how many times you recount, the numbers don't add up. You wake up in a mild sweat, relieved that it was just a dream.
It's the surgical tech version of the actor's nightmare about forgetting their lines. It means you care. It means you take your job seriously. And it means you're definitely not alone.
The Deep Respect for the Circulator Who Has Your Back
A great circulator makes all the difference during count. They double-check with you. They help you search when something's missing. They document clearly, they communicate calmly, and they never make you feel like you're in it alone.
The surgical tech and circulator relationship during count is a partnership. When it works well, it's seamless. When it doesn't, the whole case feels harder. You remember the circulators who had your back, and you're grateful for every single one of them.
Why the Count Matters More Than Anyone Outside the OR Realizes
To someone outside the operating room, counting sponges and instruments might sound tedious. Repetitive. Maybe even boring. But to you, it's patient safety. It's professional accountability. It's the difference between a successful case and a preventable complication.
You've seen the protocols. You've read the incident reports. You know that retained surgical items, while rare, can cause serious harm — infection, reoperation, prolonged recovery. The Joint Commission tracks these events, and every single one is preventable with accurate counts.
So you count. You recount. You verify. You document. You stay vigilant even when you're tired, even when the case runs long, even when it's the fifth procedure of the day. Because that's what surgical techs do.
If this list made you nod along — or laugh, or feel a little bit seen — you're part of a community that gets it. If you're exploring new OR opportunities or looking for a facility that values the precision and dedication you bring to every case, reach out to us at contact@intuites.healthcare and let us know what kind of surgical tech role you're looking for.
Sources
Ready for your next allied health assignment?
Browse open allied health jobs across the US — weekly pay, stipends, and a recruiter who reads every application.